Most people have never heard of koseri bacteria until a lab report puts it in front of them, usually after a urine culture or, in more frightening cases, after a newborn gets sick. That gap between “never heard of it” and “now I need to understand it fast” is exactly where this guide lives.
Citrobacter koseri is a gram-negative bacterium that normally lives quietly in the human gut. Most of the time it causes no trouble at all. But under the wrong conditions, in a premature infant, an older adult with a catheter, or anyone with a weakened immune system, it can turn into a serious infection. In rare neonatal cases, it’s linked to some of the most severe brain infections a newborn can get.
I’m not a microbiologist by training, but I’ve spent a lot of time reading clinical case reports and lab manuals to put this together, and I’ll be upfront about where the evidence is thin. Some of what’s known about C. koseri comes from case reports rather than large trials, simply because the infection is uncommon. That matters for how confidently we can talk about specifics like exact mortality rates.
What Is koseri bacteria?
Citrobacter koseri, formerly called Citrobacter diversus, belongs to the Enterobacteriaceae family, the same broad group that includes E. coli and Salmonella. It’s a rod-shaped organism that moves using small tail-like structures called flagella, and it can survive with or without oxygen, which microbiologists call being a facultative anaerobe.
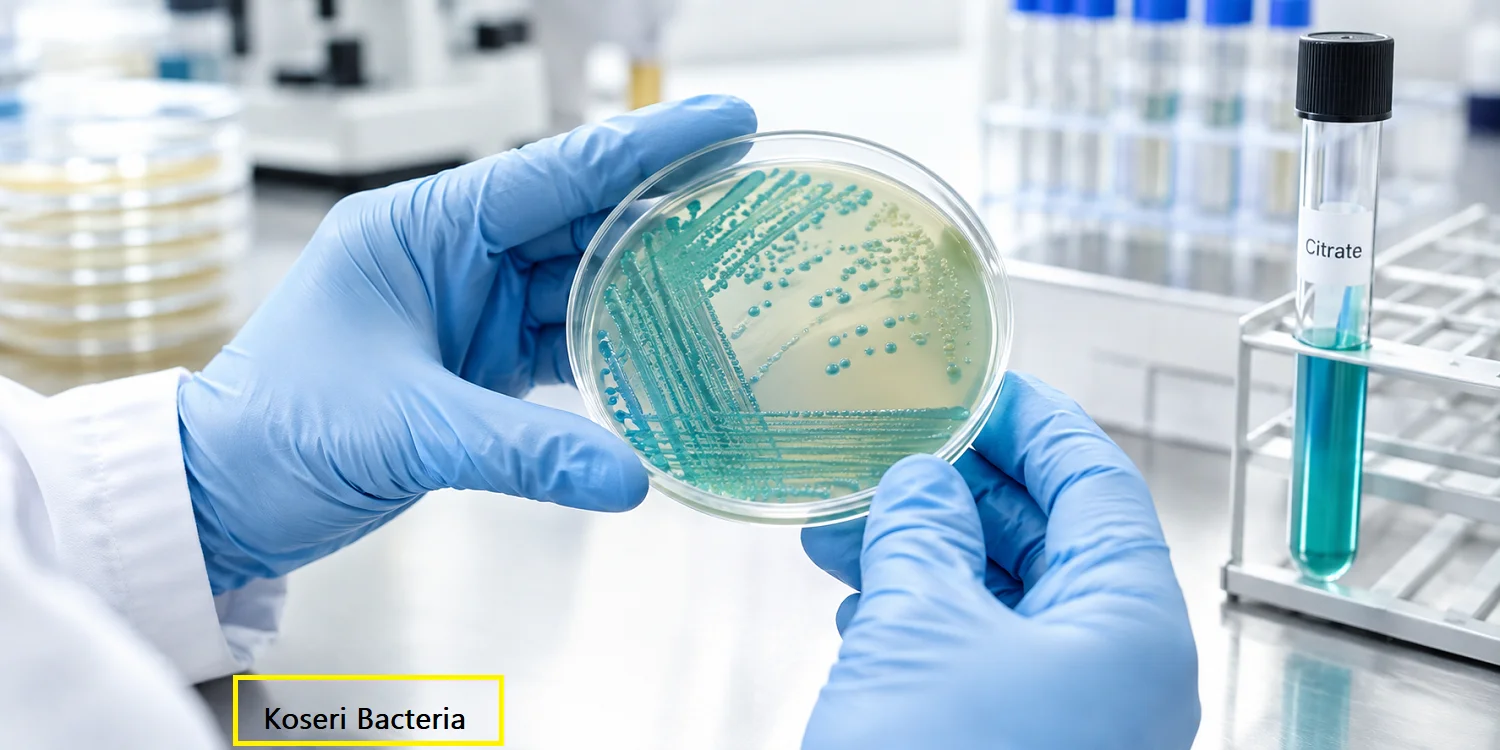
Here’s the detail that gives the bacterium its name: it can survive using citrate as its only carbon source. Lab technicians actually use this trait to help identify it. When grown on a specific test medium (Simmons’ citrate agar), the bacteria turn the medium from green to blue as they consume the citrate. It’s a small, elegant test with a big payoff for diagnosis.
Where does it come from? Soil, water, and food are all natural homes for it. It’s also part of the normal bacterial population in the intestines of humans and animals. So on any given day, plenty of healthy people are carrying it without any symptoms at all. The organism only becomes a problem when it ends up somewhere it shouldn’t be, like the bloodstream, the urinary tract, or the brain.
Who Gets Sick From It, and Why
This is the part that surprises people: C. koseri rarely causes disease in healthy adults. Researchers often describe it as having low virulence, meaning it’s not naturally aggressive. So why does it show up in some of the scariest case reports in pediatric medicine?
The answer comes down to opportunity. Three groups face the highest risk:
Newborns, especially premature infants. This is where C. koseri has its most serious reputation. It’s one of the leading causes of a rare form of neonatal meningitis, and unusually, it has a strong tendency to cause brain abscesses in infected infants, something most other bacteria causing meningitis don’t do nearly as often.
Older adults, particularly those with urinary catheters. Hospitalized elderly patients, especially men with indwelling catheters, make up a large share of adult C. koseri infections. Most of these show up as urinary tract infections.
People with weakened immune systems. Chemotherapy patients, transplant recipients, and anyone with a condition that suppresses immune function are more vulnerable to this organism finding a way in.
One case I came across involved a 76-year-old man with severe asthma whose C. koseri meningitis was ultimately traced back to an intestinal parasite infection that let the bacteria cross into his bloodstream. It’s a good reminder that this organism rarely acts alone. It tends to take advantage of a body that’s already compromised somewhere else.
How Infection Happens
In newborns, transmission can happen two ways. It can pass from mother to baby before birth, what’s called vertical transmission, or it can spread after birth through contact with colonized staff or equipment in a neonatal unit, known as horizontal transmission. Neither route is common, but outbreaks in neonatal intensive care units have been documented, which is why infection control in these units takes bacterial colonization seriously even when no one is currently sick.
In adults, the paths in are more mundane: contaminated urinary catheters, existing GI tract colonization spreading to a wound or the bloodstream, or, less commonly, aspiration into the lungs. Hospital-acquired infection is far more typical than community-acquired infection for this bacterium. That single fact tells you most of what you need to know about who’s at risk: people already in a hospital bed, already vulnerable, already exposed to more invasive equipment.
Symptoms to Watch For
Symptoms depend heavily on where the infection sets up. There isn’t one universal warning sign, which is part of what makes this bacterium tricky.
In neonates, the picture is often subtle and easy to miss early. Watch for:
- Fever or, just as often, an unstable or low temperature
- Poor feeding or noticeable lethargy
- Seizures
- Apnea, meaning pauses in breathing
- A bulging fontanelle, the soft spot on a baby’s skull
That last one is a red flag clinicians take seriously, since it can point toward pressure building in the brain. Interestingly, classic signs like a stiff neck or high fever, things you’d expect with meningitis, are often absent in infected newborns. That absence is exactly why the diagnosis gets missed or delayed sometimes. If you’re a new parent and something feels wrong even without a textbook symptom, trust that instinct enough to get it checked.
In adults, symptoms map more closely to the infection site:
- Urinary tract infection: burning during urination, urgency, cloudy or foul-smelling urine
- Bloodstream infection (bacteremia): fever, chills, rapid heart rate, confusion
- Respiratory infection: cough, shortness of breath, fever
- Abdominal infection: pain, fever, digestive upset
Skin infections from this bacterium are uncommon but not unheard of. Case reports describe folliculitis, cellulitis, and even one unusual case of bullous erysipelas, a blistering skin infection, which just goes to show this organism doesn’t always follow the expected script.
Diagnosis: How Labs Confirm It
Diagnosis starts with a sample, blood, urine, cerebrospinal fluid, or wound fluid, depending on where the infection is suspected. From there, the process is fairly standard microbiology:
- Gram staining shows gram-negative rods under the microscope, though this only narrows things down; it doesn’t confirm the species.
- Culturing on blood agar or MacConkey agar lets the bacteria grow into visible colonies, usually within a day or two.
- Biochemical testing does the real identification work. The citrate test mentioned earlier is one piece; labs also check indole production, urease activity, and several fermentation reactions to distinguish C. koseri from close relatives like Citrobacter freundii.
- Antibiotic susceptibility testing comes last, and it’s arguably the most clinically important step, since it tells doctors which drugs will actually work.
That last point matters more than it might seem. This isn’t a bacterium you can treat on autopilot.
Treatment and Antibiotic Resistance
Here’s something that catches a lot of people off guard: C. koseri carries a gene that can produce an enzyme called AmpC beta-lactamase, which breaks down certain antibiotics before they get a chance to work. Add in the possibility of additional resistance genes riding on mobile genetic elements, and you get an organism that doesn’t respond predictably to whatever antibiotic is sitting on the shelf.
That’s exactly why susceptibility testing isn’t optional. A 2014 review of C. koseri treatment noted that clinicians have used aminoglycosides, carbapenems, cephalosporins, chloramphenicol, and quinolones, but which one actually works varies by strain and by patient. There’s no single first-line answer here. Doctors treat this bacterium the way you’d want a mechanic to treat an unfamiliar engine: test it before you commit to a fix.
For serious infections like meningitis or brain abscesses, treatment usually means an extended course of IV antibiotics, sometimes combined with drainage if an abscess has formed. Recovery can take weeks, not days, and in one case I read about, a toddler completed 21 days of one antibiotic and 16 days of a second before being discharged. That’s a long road for a bacterium most people will go their whole lives never having heard of.
Why Brain Abscesses Are the Biggest Concern
I want to spend a moment on this because it’s the detail that separates C. koseri from most run-of-the-mill opportunistic bacteria. When it causes meningitis in infants, it’s unusually prone to also causing brain abscesses, and the combination carries a genuinely high risk of complications and death, particularly in neonates.
Researchers still don’t fully understand why. One theory points to a specific surface protein that may act as a virulence factor in the strains most likely to cause abscesses. There’s also research into a gene cluster tied to iron transport, sometimes called a high-pathogenicity island, that appears specifically in C. koseri and not in other Citrobacter species. Whether that fully explains the abscess pattern is still being studied. I’ll be honest: this is one of those areas where the science is evolving, and I’d rather say “still under investigation” than pretend the mechanism is fully settled.
What this means practically: if a newborn is diagnosed with C. koseri meningitis, doctors typically order brain imaging even without obvious signs of an abscess, because catching one early changes the treatment plan significantly.
Prevention: What Actually Helps
Since most C. koseri infections are hospital-acquired, prevention leans heavily on infection control rather than anything an individual can do at home. Still, a few things are worth knowing:
- In neonatal units, strict hand hygiene among staff and prompt investigation of any cluster of infections helps catch outbreaks early, since horizontal transmission from asymptomatic staff has been documented before.
- For catheterized patients, minimizing catheter duration and following sterile insertion protocols reduces the entry points bacteria have.
- For immunocompromised patients generally, standard precautions around hand hygiene and food safety apply, the same advice you’d give for avoiding any opportunistic infection.
There’s no vaccine for this bacterium, and given how rarely it causes disease in healthy people, that’s not likely to change soon. The more realistic goal is catching it fast in the people who are actually vulnerable.
Conclusion
Citrobacter koseri is a strange case in microbiology: a normally harmless gut resident that, in the wrong host, becomes capable of some of the most serious infections in medicine, especially neonatal meningitis with brain abscess. For most healthy adults, it’s a non-issue. For newborns, older hospitalized patients, and anyone immunocompromised, it deserves to be taken seriously, tested properly, and treated based on actual susceptibility results rather than guesswork.
If there’s one thing worth remembering from all of this, it’s that absence of “classic” symptoms doesn’t mean absence of infection, particularly in infants. When something seems off, especially with a newborn, that’s worth acting on even before every textbook sign shows up. Talk to a physician or pediatrician if you have specific concerns about a diagnosis or symptoms you’re seeing; this article is meant to help you understand the bacterium, not to replace medical care.
Sources Cited
- Wikipedia — Citrobacter koseri (tertiary overview, general reference): https://en.wikipedia.org/wiki/Citrobacter_koseri
- Journal of Clinical Microbiology — “Biochemical identification of citrobacteria in the clinical laboratory” (Janda et al., 1994), peer-reviewed primary source on lab identification: https://pmc.ncbi.nlm.nih.gov/articles/PMC263890